R.노두현정형외과와 연구 이야기
글자
← 연구 이야기

관절염 검사와 경과 · 2026

X-ray와 MRI는 관절염의 다른 면을 보여줍니다

같은 무릎을 오래 추적해 보니, 연골과 반월상연골의 변화는 위치에 따라 다른 순서로 관찰됐습니다.

Knee Surgery, Sports Traumatology, Arthroscopy · Do Weon Lee, Ji-Sahn Kim, Hyuk-Soo Han, Du Hyun Ro

원문 Figure 1

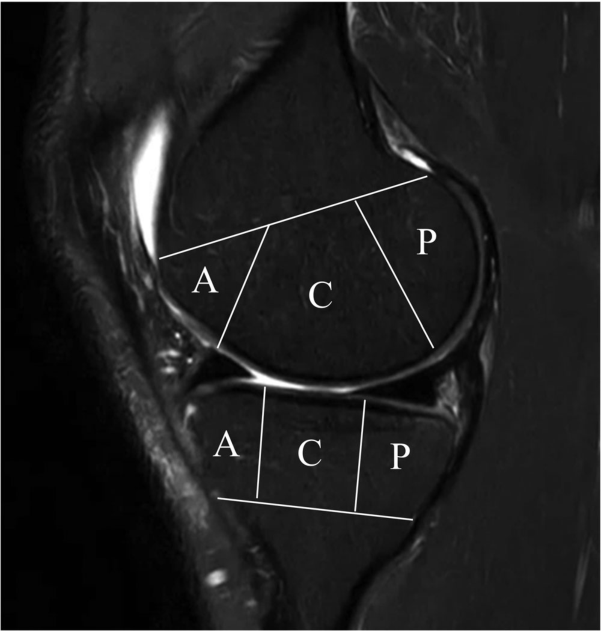
MRI에서 대퇴골과 경골을 앞(A)·가운데(C)·뒤(P)로 나눕니다. 같은 무릎도 위치에 따라 조직 변화의 양상이 달라질 수 있어 구획을 나누어 분석했습니다.그림 크게 보기

MRI에서 대퇴골과 경골을 앞(A)·가운데(C)·뒤(P)로 나눕니다. 같은 무릎도 위치에 따라 조직 변화의 양상이 달라질 수 있어 구획을 나누어 분석했습니다.

Do Weon Lee, Ji-Sahn Kim, Hyuk-Soo Han, Du Hyun Ro. Longitudinal correlation between X-ray and MRI findings in medial compartment knee osteoarthritis: Insights into early cartilage loss and structural changes. Knee Surgery, Sports Traumatology, Arthroscopy. 2026;34(6):2047–2056. https://doi.org/10.1002/ksa.70016. © 2025 The Author(s).

근거·원문그림 이용조건
원문 캡션

Figure 1

01

X-ray 간격에는 연골판의 영향도 담깁니다

X-ray에서 뼈 사이 간격이 좁아졌다고 설명할 때가 많습니다. 하지만 그 간격은 연골 하나만의 두께를 보여주는 값이 아닙니다. 연골판의 위치와 손상, 촬영 자세도 관련됩니다. MRI는 연골·연골판·골수 병변을 더 구체적으로 나누어 볼 수 있습니다. 두 검사에서 얻는 정보가 시간에 따라 어떻게 연결되는지 살핀 연구입니다.

02

같은 무릎을 위치별로 나누었습니다

MOST의 7년 관찰 자료에서 3,710무릎을 분석했습니다. MRI에서 중앙과 뒤쪽 구획을 나누고 연골 손상, 연골판 손상·돌출, 뼈의 변화를 X-ray 등급과 비교했습니다. 그림의 A·C·P는 앞·중앙·뒤를 뜻합니다. 한 무릎 안에서도 위치가 다르면 변화 양상이 같지 않다는 점을 확인하기 위한 구분입니다.

03

중앙과 뒤쪽에서 다른 양상이 관찰됐습니다

중앙에서는 연골 변화가 먼저 나타나는 양상, 뒤쪽에서는 연골판 변화가 먼저 나타나는 양상이 관찰됐습니다. X-ray에서는 경골의 골극이 비교적 이른 소견이었습니다. 그림의 각 등급에 놓인 상자와 점은 집단의 분포입니다. 이를 모든 환자에게 똑같이 진행되는 순서나 정확한 시간표로 읽으면 안 됩니다.

원문 Figure 2
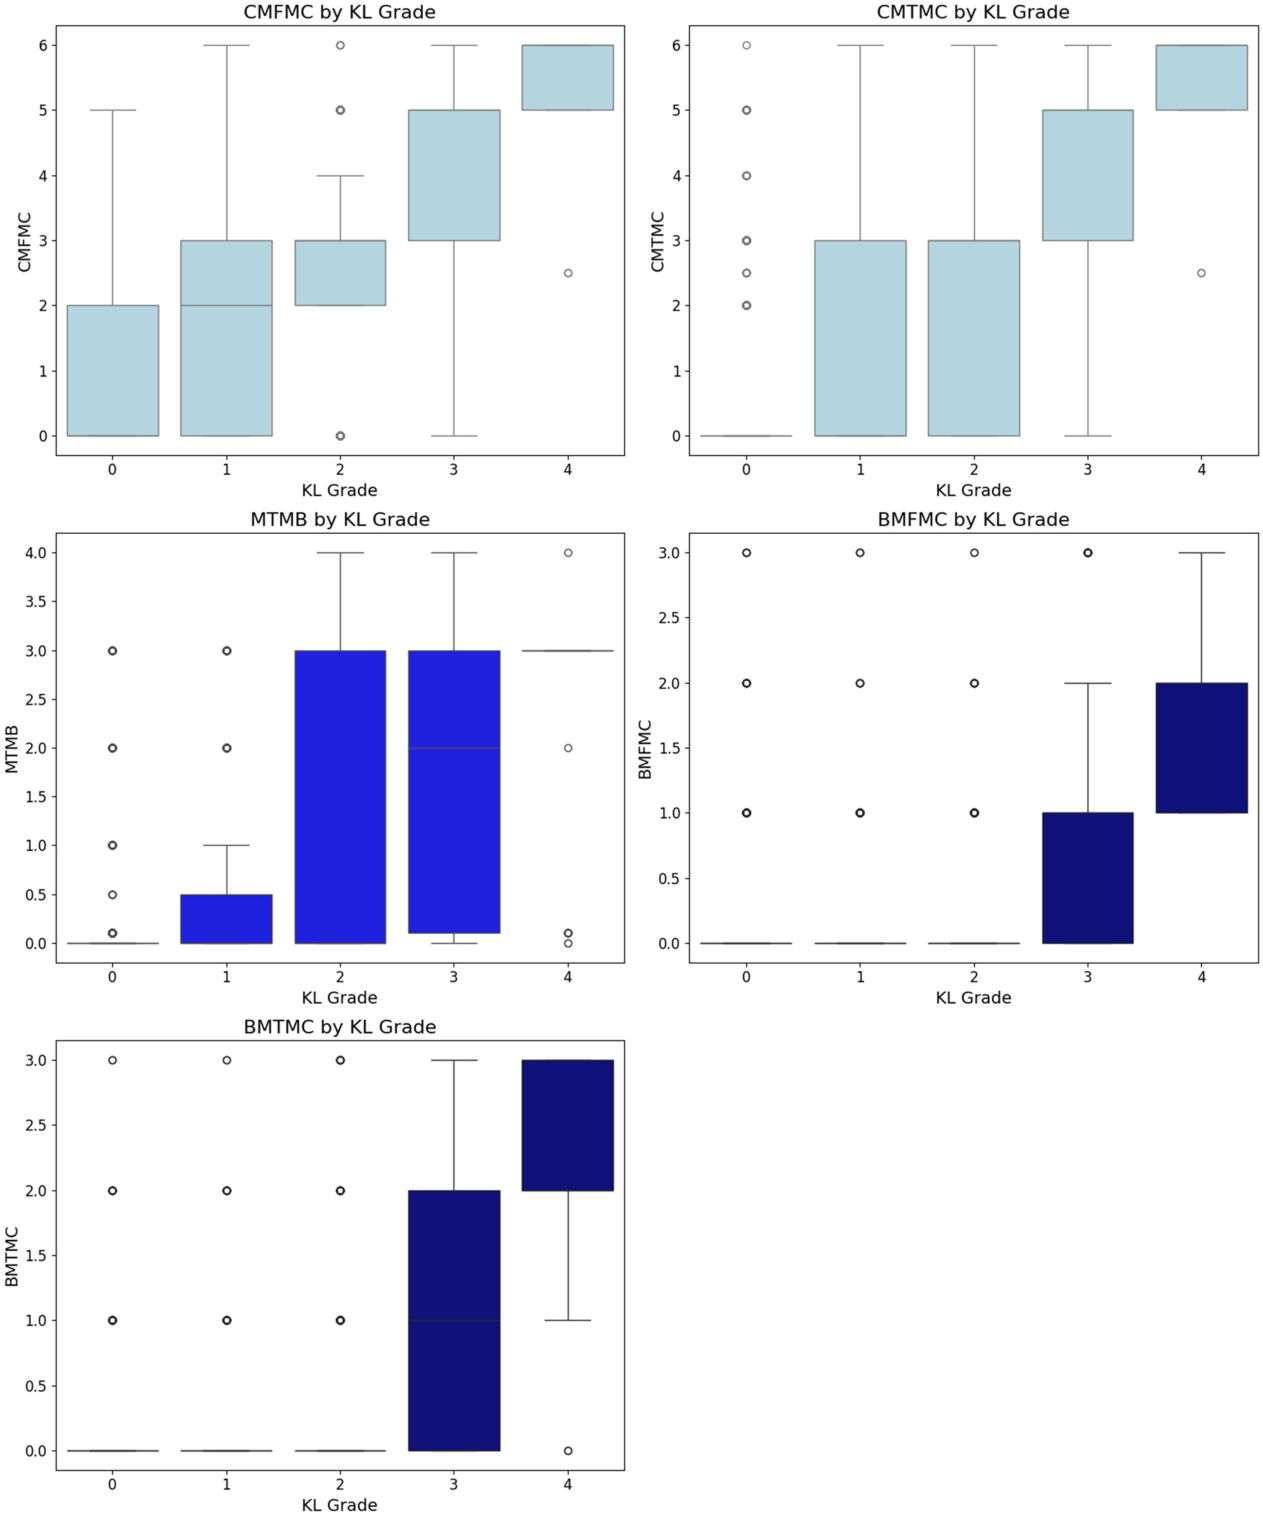
X-ray KL 등급별 중앙 구획의 연골·연골판·골수 MRI 소견을 비교합니다.그림 크게 보기

X-ray KL 등급별 중앙 구획의 연골·연골판·골수 MRI 소견을 비교합니다.

Do Weon Lee, Ji-Sahn Kim, Hyuk-Soo Han, Du Hyun Ro. Longitudinal correlation between X-ray and MRI findings in medial compartment knee osteoarthritis: Insights into early cartilage loss and structural changes. Knee Surgery, Sports Traumatology, Arthroscopy. 2026;34(6):2047–2056. https://doi.org/10.1002/ksa.70016. © 2025 The Author(s).

원문 캡션

Figure 2

04

연골판 돌출이 중요하게 나타났습니다

연골판이 관절 바깥쪽으로 밀려난 돌출은 이후 진행과 관련된 지표 중 가장 강한 연관성을 보였습니다. 연골 손상과 연골판 파열도 관련됐습니다. 그렇다고 돌출만 없애면 관절염이 멈춘다는 치료 효과를 증명한 것은 아닙니다. 영상에서 확인한 관계를 다음 연구와 임상 평가에 연결하는 근거입니다.

05

관절염이면 모두 MRI를 찍어야 할까요?

이 결과만으로 모든 환자의 정기 MRI 촬영을 권하지 않습니다. 일반적인 골관절염 평가에는 증상과 진찰, 필요한 X-ray가 중요합니다. 설명하기 어려운 증상이나 다른 손상 의심 등 구체적인 임상 질문이 있을 때 추가 검사 필요성을 판단합니다. 연구에서는 자세한 조직 정보를, 진료에서는 검사로 해결할 질문을 먼저 정해야 합니다.

연구 숫자 다시 보기

3,710분석에 포함한 무릎
7년MOST 관찰 자료
앞·중앙·뒤나누어 본 구획
RESEARCH FINDING무릎

연구 대상의 구성

분석에 포함한 무릎
3,710
02,1334,267
연구에 포함된 자료의 수입니다. 치료의 효과나 개인의 위험 확률을 나타내지 않습니다.

많이 묻는 질문

이 결과를 개인의 치료에 바로 적용할 수 있나요?

이 결과만으로 모든 환자의 정기 MRI 촬영을 권하지 않습니다. 일반적인 골관절염 평가에는 증상과 진찰, 필요한 X-ray가 중요합니다. 설명하기 어려운 증상이나 다른 손상 의심 등 구체적인 임상 질문이 있을 때 추가 검사 필요성을 판단합니다. 연구에서는 자세한 조직 정보를, 진료에서는 검사로 해결할 질문을 먼저 정해야 합니다.

연구 방법과 수치 자세히 보기

Longitudinal correlation between X-ray and MRI findings in medial compartment knee osteoarthritis: Insights into early cartilage loss and structural changes

대상과 방법

3,710 knees; 원래 MOST 코호트의 연령은 50–79세입니다.

MOST의 7년 추적 자료를 이용했습니다. 같은 시점의 X-ray와 MRI가 있는 내측 OA 중심 무릎에서 영상 소견을 비교하고 종단 회귀를 시행했습니다.

논문에 보고된 결과

  1. 중앙부에서는 연골손상 후 반월상연골·골 변화가, 후방부에서는 반월상연골 변화가 먼저 관찰됐습니다. 중앙 대퇴 연골 소실은 KL 0에서도 관찰됐습니다.
  2. X-ray 변화는 경골 골극 → 관절간격 협소 → 대퇴 골극 순이었습니다. 반월상연골 돌출·연골 소실·반월상연골 파열이 진행과 연관됐고(P < 0.001), 돌출의 연관성이 가장 강했습니다.

해석의 범위

관찰된 상관관계로 병리적 인과 순서를 단정할 수 없습니다. MRI가 수술 결과를 개선하거나 모든 KL 0 환자에게 필요함을 검증한 것은 아닙니다.

Keywords · 주제어

Abstract · 원문 초록

Do Weon Lee, Ji-Sahn Kim, Hyuk-Soo Han, Du Hyun Ro. Longitudinal correlation between X-ray and MRI findings in medial compartment knee osteoarthritis: Insights into early cartilage loss and structural changes. Knee surgery, sports traumatology, arthroscopy : official journal of the ESSKA. 2026;34(6):2047-2056. doi:10.1002/ksa.70016.

PURPOSE

Knee osteoarthritis (OA) is a common joint disorder assessed using radiographic (X-ray) and magnetic resonance imaging (MRI). While X-rays are accessible, MRI provides detailed insights into meniscus and cartilage. Few studies have evaluated the correlation between X-ray and MRI findings in knee OA longitudinally. This study addresses this gap by investigating their relationship over time.

METHODS

The Multicenter Osteoarthritis Study (MOST) dataset, a public, longitudinal cohort study focusing on knee OA in older adults, was used. The analysis included 3710 knees with medial compartment OA from different follow-ups over the course of 7 years. X-ray findings were compared with MRI findings, encompassing cartilage, meniscal and bone pathologies.

RESULTS

In the central compartment, knee OA progression began with cartilage loss, followed by meniscal and bone pathology, while in the posterior compartment, meniscal changes preceded cartilage and bone lesions. Cartilage loss in the central femur was the earliest event, even in Kellgren-Lawrence grade 0 knees, preceding X-ray changes. Tibial osteophytes developed first on X-ray, followed by joint space narrowing and femoral osteophytes. Longitudinal regression identified meniscal extrusion, cartilage loss and meniscal tear as significant predictors of OA progression (p < 0.001), with meniscal extrusion being the strongest.

CONCLUSION

Knee OA progression differs by compartment, with cartilage loss initiating changes centrally and meniscal pathology leading posteriorly. Tibial osteophytes appear early on X-ray. Meniscal extrusion is the strongest predictor of OA progression, highlighting the importance of MRI in identifying early changes and guiding personalised management.

LEVEL OF EVIDENCE

Level II.

© 2025 The Author(s). Knee Surgery, Sports Traumatology, Arthroscopy published by John Wiley & Sons Ltd on behalf of European Society of Sports Traumatology, Knee Surgery and Arthroscopy.