R.Du Hyun Ro整形外科と研究の話
文字
← 研究 の 歴史

関節炎検査と監視 · 2024

膝前方の骨の溝は、どこが浅いのでしょうか?

膝蓋骨が動く溝を3次元の領域に分けると、特に近位部で形態の違いが明らかになりました。

Knee Surgery, Sports Traumatology, Arthroscopy · Joon Young Lee, Sung Eun Kim, Oh Hyo Kwon, Youngjun Kim, Tae-Geun Son, Hyuk-Soo Han, Du Hyun Ro

原図Figure 2

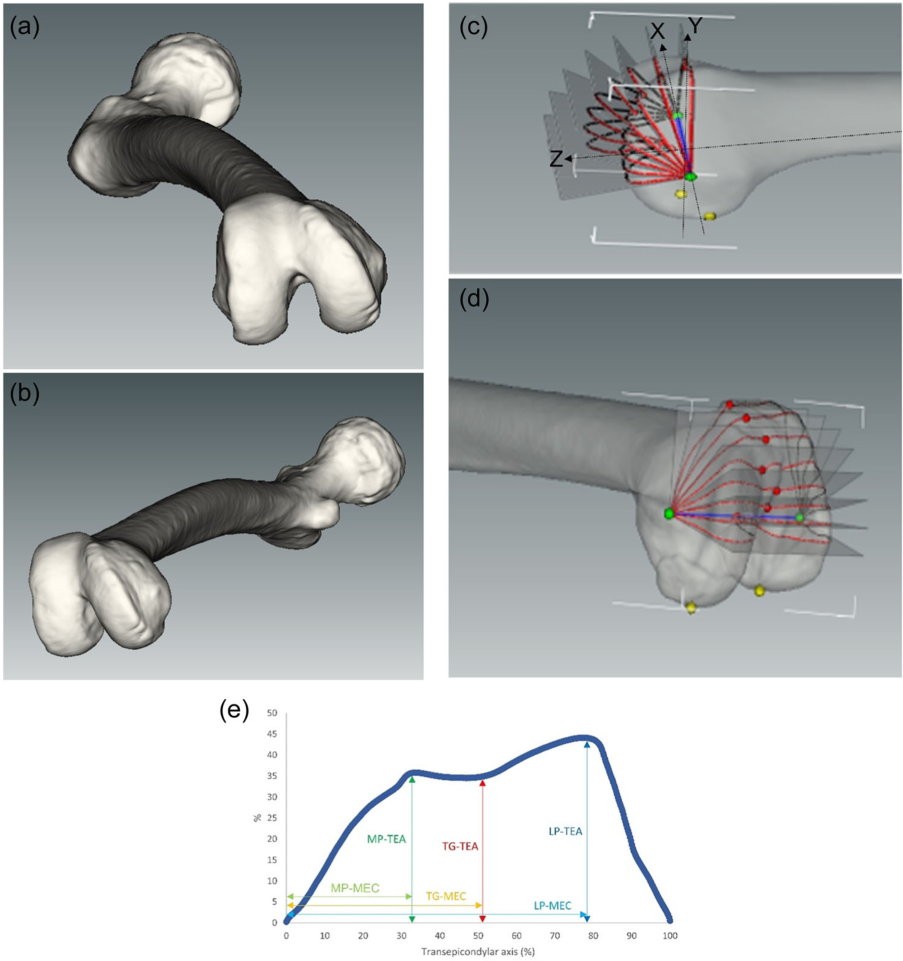
3DCTを使って弓の形を再現し安定した軸を採取して各高さのパーツを比較します 横写真で見られる分類よりも狭い場所を表す方法です図を拡大する

3DCTを使って弓の形を再現し安定した軸を採取して各高さのパーツを比較します 横写真で見られる分類よりも狭い場所を表す方法です

Joon Young Lee, Sung Eun Kim, Oh Hyo Kwon, Youngjun Kim, Tae-geun Son, Hyuk-Soo Han, Du Hyun Ro. Shallow trochlear groove and narrow medial trochlear width at the proximal trochlea in patients with trochlear dysplasia: A three-dimensional computed tomography analysis. Knee Surgery, Sports Traumatology, Arthroscopy. 2024;32(6):1434–1445. https://doi.org/10.1002/ksa.12166.

根拠・原著画像の利用条件
原著の図の説明

Figure 2

01

膝蓋骨の動きが見えます

膝蓋骨は大腿骨末端の溝「滑車」を動きます。浅い溝や形の違いは膝蓋骨不安定性と関連し得ますが、前方膝痛のすべてが滑車形成不全ではありません。この研究は治療比較より、形態の正確な記述を目指します。

02

3DCTの複数の画像を比較しました

滑車形成不全20人・対照40人の3D CTを再構成しました。一定の骨軸で0–105°を15°間隔の8断面に分け、溝深さ・内外側幅を同じ基準で測り、目視分類の差を減らし部位特徴を記述します。

03

特に上層のアーチで違いが顕著でした

形成不全群では近位、つまり上方の滑車で溝が浅く、内側幅が狭くなっていました。すべての高さで同じ差ではないため、断面位置の表示が重要です。モデルと軸はどこで距離を測ったかを示し、数値の意味を理解する出発点になります。

原図Figure 3

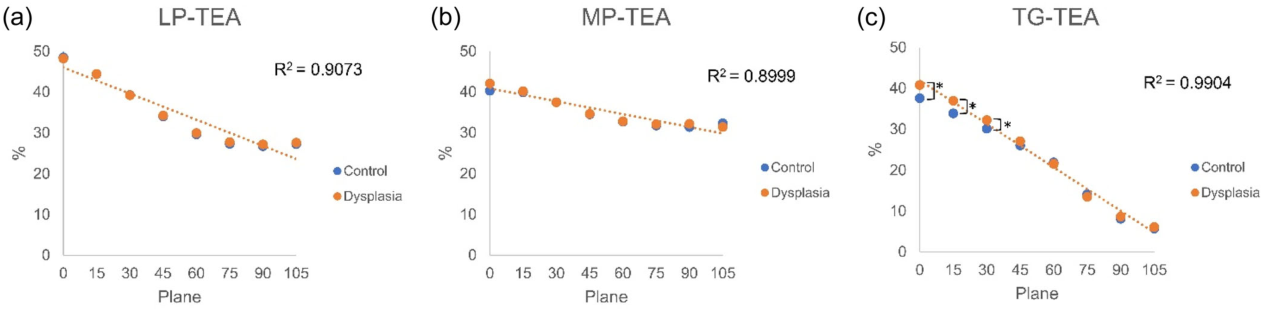
角が変化するときに gradientパターンがどのように変わるのかを比較します 測定位置が異なる場合,同じ名前を持つ指標は別の値を生成することができます.図を拡大する

角が変化するときに gradientパターンがどのように変わるのかを比較します 測定位置が異なる場合,同じ名前を持つ指標は別の値を生成することができます.

Joon Young Lee, Sung Eun Kim, Oh Hyo Kwon, Youngjun Kim, Tae-geun Son, Hyuk-Soo Han, Du Hyun Ro. Shallow trochlear groove and narrow medial trochlear width at the proximal trochlea in patients with trochlear dysplasia: A three-dimensional computed tomography analysis. Knee Surgery, Sports Traumatology, Arthroscopy. 2024;32(6):1434–1445. https://doi.org/10.1002/ksa.12166.

原著の図の説明

Figure 3

04

実際の形式と分類を結びつける研究です

Dejour分類は重要な臨床道具ですが、画像の質や読影者によって判断が異なることがあります。3次元定量指標を併用すると、同じ分類内の部位差を研究できます。術後再脱臼リスクや症状をどの程度説明できるかは追加検証が必要です。

05

CTは全ての患者には必要ありません

研究でCTを使っても、前方膝痛の全員に必要ではありません。被ばくと検査目的を考え、反復脱臼・手術計画の問いに診察や他画像から判断します。治療は滑車形状だけでなく膝蓋骨位置、靱帯、下肢アライメントも考慮します。

また研究番号を見てください

20滑車形成不全の患者
40比較対照群
8比較した断面
RESEARCH FINDING膝

研究対象の構成

滑車形成不全の患者
20
01223
研究に含まれた資料の数です。治療効果や個人のリスク確率を示しません。

よくある質問

これらの結果は 個々の治療に直接適用できるでしょうか?

研究でCTを使っても、前方膝痛の全員に必要ではありません。被ばくと検査目的を考え、反復脱臼・手術計画の問いに診察や他画像から判断します。治療は滑車形状だけでなく膝蓋骨位置、靱帯、下肢アライメントも考慮します。

方法と数値を詳しく見る

Shallow trochlear groove and narrow medial trochlear width at the proximal trochlea in patients with trochlear dysplasia: A three-dimensional computed tomography analysis

対象と方法

トロクレア症候群の20人と 40人の健康患者

3D CT再構成でTEA・MEC関連の6距離を、0–105°の8平面で15°間隔に測定しました。

論文に報告された結果

  1. 滑車形成不全群では、0°・15°・30°の断面でTG-TEAとMP-MECが大きくなっていました(すべてP < 0.05)。
  2. 0–30°の近位滑車で、滑車溝が浅く、内側滑車の幅が狭いことが報告されました。

解釈できる範囲

形態を調べた研究です。Trochleoplasty・MPFL・TTOの手技の効果は比較していません。形成不全の患者さんは20人で、サブタイプへの一般化には限界があります。

Keywords・キーワード

Abstract・原文の抄録

Joon Young Lee, Sung Eun Kim, Oh Hyo Kwon, Youngjun Kim, Tae-Geun Son, Hyuk-Soo Han, Du Hyun Ro. Shallow trochlear groove and narrow medial trochlear width at the proximal trochlea in patients with trochlear dysplasia: A three-dimensional computed tomography analysis. Knee surgery, sports traumatology, arthroscopy : official journal of the ESSKA. 2024;32(6):1434-1445. doi:10.1002/ksa.12166.

PURPOSE

Although the Dejour classification is the primary classification system for evaluating trochlear dysplasia, concerns have been raised about its reliability owing to its qualitative criteria and challenges associated with obtaining accurate radiographs. This study aimed to quantify trochlear dysplasia using three-dimensional (3D) computed tomography (CT) reconstruction with novel parameters related to the transepicondylar axis (TEA).

METHODS

Sixty patients were enrolled, including 20 with trochlear dysplasia and 40 healthy controls. The 3D CT model was generated using the Materialise Interactive Medical Image Control System software. The following six parameters were measured in eight consecutive planes at 15° intervals (planes 0-105): the distance from the TEA to the most cortical point of the lateral condyle ('LP-TEA', where LP stands for lateral peak), medial condyle ('MP-TEA', MP for medial peak) and deepest point of the trochlea ('TG-TEA', TG for trochlear groove). The distances from the medial epicondyle (MEC) to the corresponding TEA points were measured ('LP-MEC', 'MP-MEC' and 'TG-MEC').

RESULTS

In the dysplasia group, TG-TEA (planes 0, 15 and 30) and MP-MEC (planes 0, 15 and 30) were significantly greater than those in the control group (all p < 0.05 for planes of TG-TEA and MP-MEC). For type A dysplasia, LP-MEC (plane 0) was greater than that in the control group. For type B dysplasia, the MP-MEC (planes 0 and 15) and TG-TEA (planes 0 and 15) were greater than those of the control group. For type D dysplasia, MP-MEC (planes 0, 15 and 30) and TG-TEA (planes 0 and 15) were elevated.

CONCLUSION

The 3D CT reconstruction analysis established a reproducible method for quantifying osseous trochlear morphology. Patients with trochlear dysplasia had a shallow TG and narrow medial trochlear width at tracking angles of 0°-30°. This finding corroborates the clinical manifestations of recurrent patellar instability that occur during early flexion.

LEVEL OF EVIDENCE

Level III.